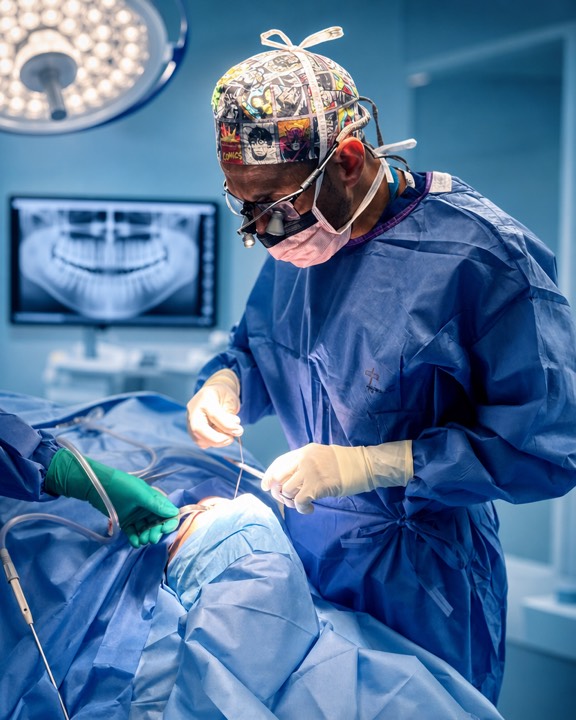
Oral surgery
Surgical dental care at our Nottingham practices, clearly explained for patients seeking treatment directly and for dentists and GPs referring their patients.
What we can treat
Dentists and GPs can refer patients for procedures that require surgical expertise, involve important structures such as nerves or the sinus, or would benefit from dedicated surgical experience.
Sherif welcomes referrals for the procedures listed below. Patients are also welcome to contact us directly to arrange a consultation, without needing a referral from their dentist or GP.
- Complex and simple extractions
- Teeth that are broken down, heavily filled, root-treated or awkwardly positioned, where a straightforward extraction is not possible.
- Wisdom tooth removal & coronectomy
- Impacted wisdom teeth, including coronectomy where roots lie close to the nerve in the lower jaw. Full details on the wisdom teeth page.
- Orthodontic tooth exposure & bonding
- Uncovering a buried tooth and attaching a bracket and chain so an orthodontist can guide it into position. Planned jointly with your orthodontist. More on exposure and bonding.
- Impacted canines & supernumerary teeth
- Canines that have failed to come through, and extra teeth that block or displace the normal dentition. More on impacted canines and supernumerary teeth.
- Bone and soft tissue grafting, including sinus lifts
- Rebuilding bone or gum where it has been lost, usually to create a secure foundation for an implant. A sinus lift raises the sinus floor in the upper back jaw to make room for bone.
- Oral biopsies
- Taking a small tissue sample from a lesion in the mouth so it can be examined and a diagnosis reached.
- Assessment & management of cysts and lesions
- Investigation and surgical treatment of cysts and other changes in the soft tissues or jaws, often first spotted on a routine dental X-ray.
- Apicectomy
- Removing the tip of a tooth root and sealing it, where infection persists after root canal treatment and re-treatment is not the answer.
- Frenectomy
- Releasing a restrictive frenum — the small band of tissue under the lip or tongue — where it is affecting function, gum health or orthodontic treatment. More on frenectomy.
- Dental implants
- Single missing teeth through to full-arch reconstruction. Full details on the dental implants page.
Your consultation
Whether you have been referred by your dentist or have contacted us yourself, treatment starts with a consultation. Nothing is carried out on the day unless it is straightforward, planned in advance and you are happy to go ahead.
What happens at the appointment
- Your history. What has been happening, how long for, what your own dentist has advised, your medical history and any medicines you take.
- An examination of the tooth or area concerned, and of the surrounding teeth, gums and soft tissues.
- Imaging where it is needed. Usually a panoramic X-ray. Where more detail matters — a root close to the nerve, a buried tooth, bone volume before an implant — a 3D CBCT scan is available on site, so it can normally be done at the same visit rather than at a separate appointment elsewhere.
- The options, explained plainly. Including doing nothing, where that is reasonable, and what each option involves, what it is likely to achieve and the risks that genuinely apply to your case.
- Anaesthetic and sedation. Whether local anaesthetic alone is appropriate, and whether IV sedation would help if you feel anxious.
- A written plan and the cost, itemised, before anything is booked.
How long it takes, and what to bring
Allow around thirty minutes. Bring a list of your medicines, details of any medical conditions, and your referral letter or any X-rays if you have them. If you have images taken elsewhere in the last year or so, bringing them may save repeating them.
You are welcome to bring someone with you, and to go away and think about it. A plan and a quotation are not a commitment, and there is no pressure to book on the day.
Frenectomy
A frenum is the small band of tissue that connects the lip or the tongue to the gum. Most cause no trouble at all. Occasionally one is tight, thick or attached low enough to restrict movement or pull on the gum, and releasing it makes a practical difference. That procedure is a frenectomy, sometimes called a frenotomy or a tongue-tie release.
When a frenectomy is worth considering
- A restrictive tongue-tie (ankyloglossia) in an older child or adult, where limited tongue movement affects speech, eating, or keeping the back teeth clean.
- A low lip attachment pulling on the gum, which can drag the gum margin away from a tooth and contribute to recession.
- A gap between the upper front teeth held open by a thick labial frenum, usually treated alongside orthodontic treatment rather than instead of it.
- A denture that will not settle, where the frenum lifts the edge each time the lip or tongue moves.
- Before or after implant treatment, where a frenum pulls on the gum around an implant and makes cleaning difficult.
Newborns with feeding difficulties are usually assessed by infant feeding services rather than in a dental practice, and are best referred there in the first instance.
What the procedure involves
A frenectomy is a short procedure carried out under local anaesthetic, so the area is completely numb. The frenum is released, and dissolvable stitches are usually placed. Most appointments take around twenty to thirty minutes, including the time needed to numb the area and talk you through the aftercare. IV sedation is available if you would find the appointment difficult, and is discussed at your consultation.
Recovery
Expect some soreness for a few days, eased by simple painkillers, and a small white patch where the tissue is healing, which is normal and not an infection. Warm salt-water rinses from the day after help. Stitches dissolve over one to two weeks. Where a tongue-tie has been released, gentle movement exercises matter, and you will be shown what to do before you leave.
Timing is often best planned with your dentist or orthodontist, and treatment is only recommended where it will make a genuine difference.
Impacted canines and supernumerary teeth
Teeth that fail to come through, and extra teeth that get in the way, are two of the more common reasons a dentist or orthodontist refers someone for surgery. Both are usually spotted on a routine dental X-ray, often in a child or teenager, and both are more straightforward to deal with when they are found early.
Supernumerary teeth
A supernumerary tooth is an extra tooth, beyond the normal set. The most common sits in the midline at the front of the upper jaw, where it is known as a mesiodens. Many cause no symptoms and are discovered by chance.
They are usually removed when they:
- block an adult tooth from coming through, most often an upper front tooth;
- crowd or displace the teeth either side, or push them out of line;
- interfere with planned orthodontic treatment;
- develop a cyst around the crown, which is uncommon but a clear reason to act.
Removal is a surgical procedure, because the tooth usually sits within the bone rather than in the mouth. It is carried out under local anaesthetic, with IV sedation available. A 3D CBCT scan is often taken first, so the position of the tooth and its relationship to the roots of the neighbouring teeth and to the nasal floor are known before starting, rather than discovered during the procedure.
Impacted canines
The upper canine is the second most commonly impacted tooth after the wisdom tooth. Rather than being removed, an impacted canine is usually worth saving: it is a strong tooth with a long root, and a good result is achievable with combined surgical and orthodontic treatment.
The usual approach is exposure and bonding. The gum and a small amount of bone over the buried tooth are lifted, a bracket with a fine gold chain is bonded to it, and the chain is left accessible so your orthodontist can apply gentle traction and guide the tooth into position over the following months. This is planned jointly with the orthodontist from the outset, so the surgery fits the orthodontic timetable rather than the other way round.
Recovery
Swelling and discomfort for a few days are usual after either procedure, with the first two to three days the most noticeable. Soft foods and simple painkillers are usually enough. Stitches are dissolvable. Orthodontic traction on an exposed canine normally begins a few weeks later, once the area has settled.
Anxiety, anaesthetic and IV sedation
Many people delay necessary procedures because they feel anxious about the appointment itself, rather than the treatment they need. This is very common, and something Sherif takes into account from the outset.
Sherif regularly treats patients who find dental treatment difficult or overwhelming. You will be given time to understand what is happening, with each stage explained before treatment begins and as it progresses. Nothing is rushed, and you can ask to stop at any point. For many patients, this calm and considered approach is all they need to feel comfortable proceeding.
Intravenous (IV) sedation
For patients who feel particularly anxious about treatment, intravenous (IV) sedation can help make the experience much more comfortable. A sedative is given through a small cannula placed in the hand or arm, and begins to work within a few minutes.
You remain conscious and able to communicate throughout treatment. IV sedation is not a general anaesthetic — it produces a deeply relaxed state. Many patients lose track of time and remember very little, if anything, about the procedure afterwards. Local anaesthetic is also used to ensure the area being treated is completely numb.
IV sedation is not suitable for everyone. Sherif will review your medical history, medications and planned treatment during your consultation to determine whether it is the right option for you.
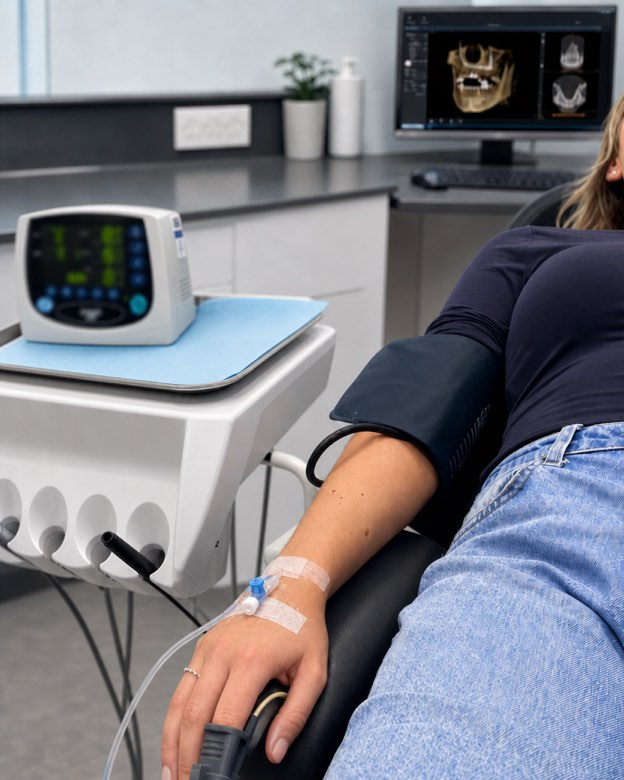
If you are sedated, you will need to arrange
- An escort A responsible adult to take you home afterwards and stay with you for the rest of the day.
- A clear 24 hours No driving, operating machinery, drinking alcohol or signing anything legally binding for a full day afterwards.
- Your medication list Bring details of everything you take, including anything bought over the counter.
- Pre-appointment instructions You will be given specific guidance on eating and drinking beforehand. Follow it exactly, or the appointment may need rescheduling.
If anxiety has been holding you back from treatment, let us know when you get in touch. It simply means we can tailor your consultation to make you feel as comfortable and at ease as possible.
Referring a patient
Sherif welcomes referrals for wisdom teeth removal, oral surgery and dental implant treatment. He works alongside referring clinicians to provide the treatment their patients need, while keeping them informed and ensuring patients return to their usual clinician for ongoing care.
What to include with your referral
- Patient’s name, date of birth and contact details
- The reason for referral and the treatment or assessment requested
- Relevant medical history and current medications
- Any available radiographs, including the date they were taken
- Any concerns about dental anxiety or treatment tolerance
What happens next
The referral is reviewed and the patient contacted to arrange a consultation. You receive a written summary of the assessment and, after treatment, a note of what was carried out and any follow-up the patient needs from you.
Questions about oral surgery
Is oral surgery safe?
Oral surgery is carried out routinely and is generally well tolerated, but like any surgery it carries risks — commonly swelling, bruising and discomfort, and less commonly infection, bleeding or altered sensation where a procedure sits near a nerve. The risks that actually apply to your case are identified from your examination and imaging and discussed with you before you decide anything.
Do you carry out orthognathic (jaw) surgery?
No. Orthognathic surgery repositions the upper or lower jaw to correct the way the jaws meet. It is carried out in hospital, under general anaesthetic, by a maxillofacial surgical team, and it usually runs alongside a course of orthodontic treatment lasting a year or more before and after the operation. It is not a procedure that can be provided in a dental practice.
If you think your bite or jaw position may need that kind of treatment, the usual route is an assessment with an orthodontist, who will refer you into a hospital joint clinic where the orthodontic and surgical plan is made together.
What can be done here is the surgery that often sits around that treatment: removing teeth needed to create space, exposing and bonding impacted teeth so they can be moved, removing supernumerary teeth, and wisdom tooth removal before or after jaw surgery. Sherif also holds a part-time post in oral and maxillofacial surgery at Coventry University Hospitals, so if a hospital referral is the right answer, you will be told plainly.
How long does a frenectomy take to heal?
Most people are comfortable within three to four days, with simple painkillers as needed. A white patch usually forms over the area as it heals, which is normal and not an infection. Dissolvable stitches disappear over one to two weeks, and the tissue settles fully over about a month.
Where a tongue-tie has been released, gentle movement exercises for the first couple of weeks help to keep the range of movement gained during the procedure. You will be shown these before you leave. More about frenectomy.
Do I need a referral to be seen?
No. Referrals from dentists and GPs are welcome, but you can contact the practice yourself and arrange a consultation directly.
Do you offer IV sedation?
Yes. IV sedation is available for patients who feel particularly anxious about treatment or would prefer additional support during their procedure. A sedative is given through a small cannula in the hand or arm, helping you feel deeply relaxed while remaining conscious and able to respond.
IV sedation is not a general anaesthetic. Many patients find that they remember very little, if anything, about the procedure afterwards. Local anaesthetic is also used to ensure the treatment area is completely numb.
Sherif will assess whether sedation is suitable for you based on your medical history, medications and planned treatment. You will also need a responsible adult to accompany you home and follow the aftercare instructions provided, and you must not drive for 24 hours. More on sedation.
Will my own dentist continue to look after me?
Yes. If you have been referred for a specific procedure, your routine dental care remains with your own dentist. Once treatment is complete, you will return to them for your ongoing care, and they will receive an update outlining the treatment provided and any recommended follow-up.
How should I prepare for surgery?
Unless you have been advised otherwise, eat normally before your appointment and continue taking your usual medications. Please bring an up-to-date list of any medicines you take.
If you are having IV sedation, you will need a responsible adult to accompany you home and follow the specific instructions provided beforehand.
Wear something comfortable and, where possible, keep the rest of your day free so you can relax and recover after your procedure.
Arrange a consultation
Whether you have been referred or are contacting us directly, your first appointment is an opportunity to assess the problem, discuss your options and decide on the most appropriate treatment for you.